
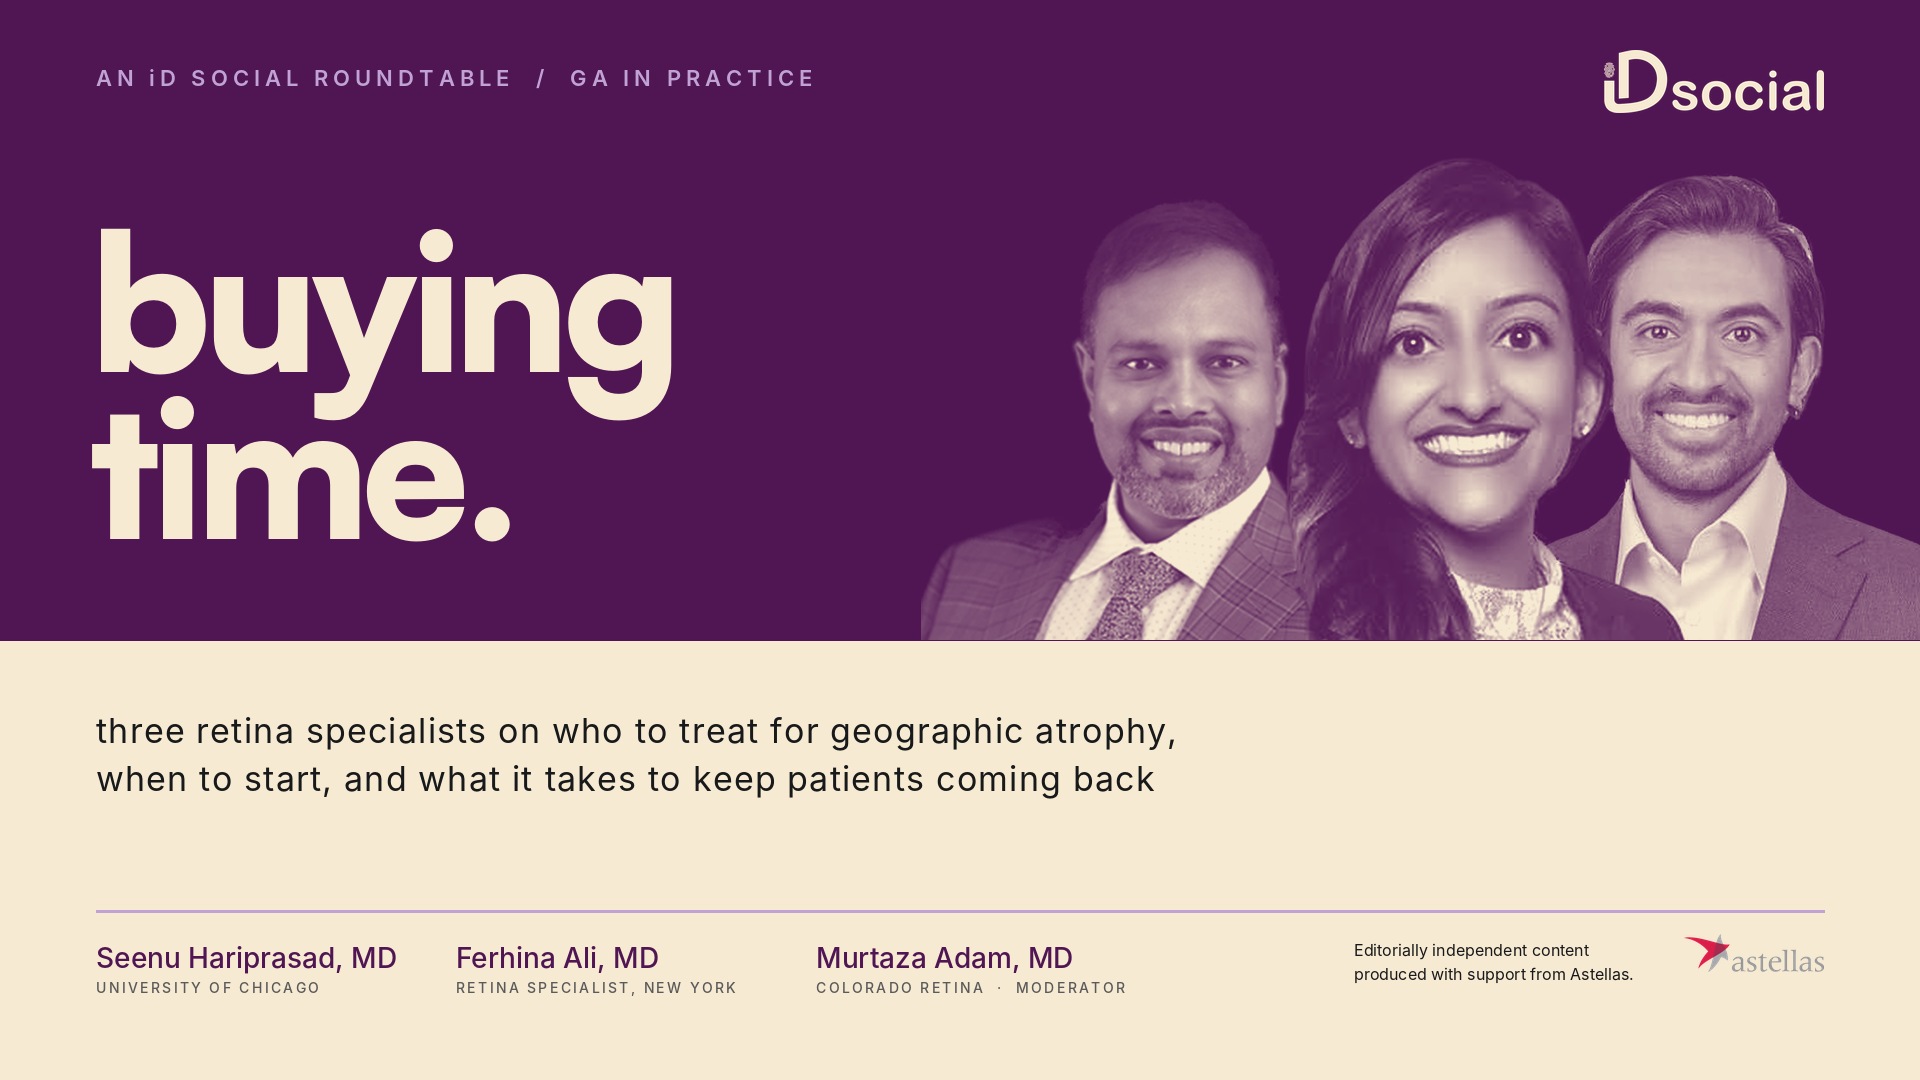

An iD Social roundtable GA in Practice

Buying time.

Three retina specialists on who to treat for geographic atrophy, when to start, and what it takes to keep patients coming back.

Buying time roundtable cover featuring Drs. Seenu Hariprasad, Ferhina Ali and Murtaza AdamWatch the roundtable on YouTube (opens in a new tab)

Editorially independent content produced with support from Astellas. For healthcare professionals.

The conversation

Explaining a benefit the patient cannot see

For most of a retina specialist’s career, geographic atrophy was a disease you watched. You measured it, imaged it, and sent the patient home with low-vision resources and a return visit in a year. The approval of pegcetacoplan and avacincaptad pegol in 2023 changed that.

Three years on, the hard part turned out not to be the injection. It is the conversation. Both pivotal programs showed a reduction in lesion growth without a difference in visual acuity at the primary time points, which means the physician has to explain a benefit the patient cannot see.

“We are not used to a disease where the patient does not know how bad they would be if they had not accepted treatment. We did not have a script for that.”
Seenu Hariprasad, MD
“Around month six to month ten, when they are not seeing a difference. That is when the questions start. It is predictable.”
Seenu Hariprasad, MD
“Initially it was driven by the patients who met me halfway.”
Ferhina Ali, MD

In the discussion

Six chapters

  1. Chapter 1

    A disease we used to watch

    How safety evidence separated the two approved agents, and what natural history data now say about how fast untreated lesions really move.

  2. Chapter 2

    The glaucoma conversation

    Explaining a benefit patients cannot see: the patient A and patient B script, functional signals beyond acuity, and early photoreceptor change.

  3. Chapter 3

    Who to treat, and why the first visit is not the day you start

    Patients who meet you halfway, bringing the household into the decision, and the case for neovascular AMD eyes already in the injection chair.

  4. Chapter 4

    The six-to-ten-month wall

    Real-world persistence data, cost and patient assistance, and the predictable moment patients start asking why they are still coming in.

  5. Chapter 5

    The patients who never reach you

    Referral gaps with optometry and general ophthalmology, and the scheduling systems that keep treated patients on track.

  6. Chapter 6

    If you are just getting started

    One pearl from each panelist for physicians beginning to treat GA.

Take back to clinic

Practice points from the panel

  • Allow time for a shared decision.Send materials home to the household, not just the patient, and bring them back once they have had time to think.
  • Use the glaucoma script.Patient A and patient B: same starting point, different trajectories at one, two and three years.
  • Expect the wall at month six to ten.Plan the reinforcement conversation before it happens, not after.
  • Say the same thing from several voices.Referring doctor, physician, fellow, technician and printed material.
  • Know the patient assistance programs.Have them ready before a patient falls into a coverage gap.
  • Educate the referrers.If the patient never reaches you, nothing else on this list matters.

Free download

Read the full roundtable

The edited discussion in full, with every chapter, the panel's practice points, financial disclosures and 15 cited references. Easy to share with your fellows, technicians and referring doctors.

Get the full discussion

The complete edited roundtable, practice points and references, as a 10-page PDF.

We'll send you future iD Social roundtables. No spam, unsubscribe anytime.

The panel

Three retina specialists

Murtaza Adam, MD
Moderator

Murtaza Adam, MD

Colorado Retina Associates, Denver

Vitreoretinal surgeon at Colorado Retina Associates in Denver. He completed fellowship training in 2017 and treats a large GA population.

Financial disclosures

Consulting, speaking, research contracts or stock ownership with Genentech, Regeneron, AbbVie, Apellis, Northgauge Healthcare Advisors, Alkeus, Neurotech, Amgen, Iveric Bio (an Astellas company), Harrow, EyeBio, REGENXBIO, EyePoint, Ocular Therapeutix, Kriya, 4DMT, Boxer Capital Management, Lumata Health and Sanro Health.


Ferhina Ali, MD
Panelist

Ferhina Ali, MD

Retina Specialist, New York

Retina specialist practicing in New York. Her research focuses on GA lesion characteristics and progression.

Financial disclosures

Consultant or advisor for 4DMT, Alkeus, Allergan, Apellis, Astellas, EyePoint, Genentech, OcuTerra, Optomed, Ocuphire, Ocular Therapeutix, Orasis, Outlook Therapeutics and Regeneron Pharmaceuticals. Speaker for Apellis and Astellas.

Seenu Hariprasad, MD
Panelist

Seenu Hariprasad, MD

University of Chicago

Chair of Ophthalmology at the University of Chicago and a vitreoretinal surgeon. He completed training in 2005 and was an early adopter of both approved complement inhibitors.

Financial disclosures

Consultant or member of the speakers bureau for AbbVie, ANI Pharmaceuticals, Astellas, Bayer, Harrow, Regeneron Pharmaceuticals, Inc., Ocular Therapeutix, Merck and Tarsus.

“I hope to use this drug on you until something better comes along.”

Murtaza Adam, MD

Watch the full roundtable on YouTube

GA in Practice is an iD Social roundtable series. This program is editorially independent and was produced with support from Astellas. The views expressed are those of the participating physicians. For healthcare professionals.

Newsletter

Get iD Social in your inbox.

Get new eyecare shows, KOL interviews, and industry highlights delivered straight to your inbox. No spam — just the content worth watching.